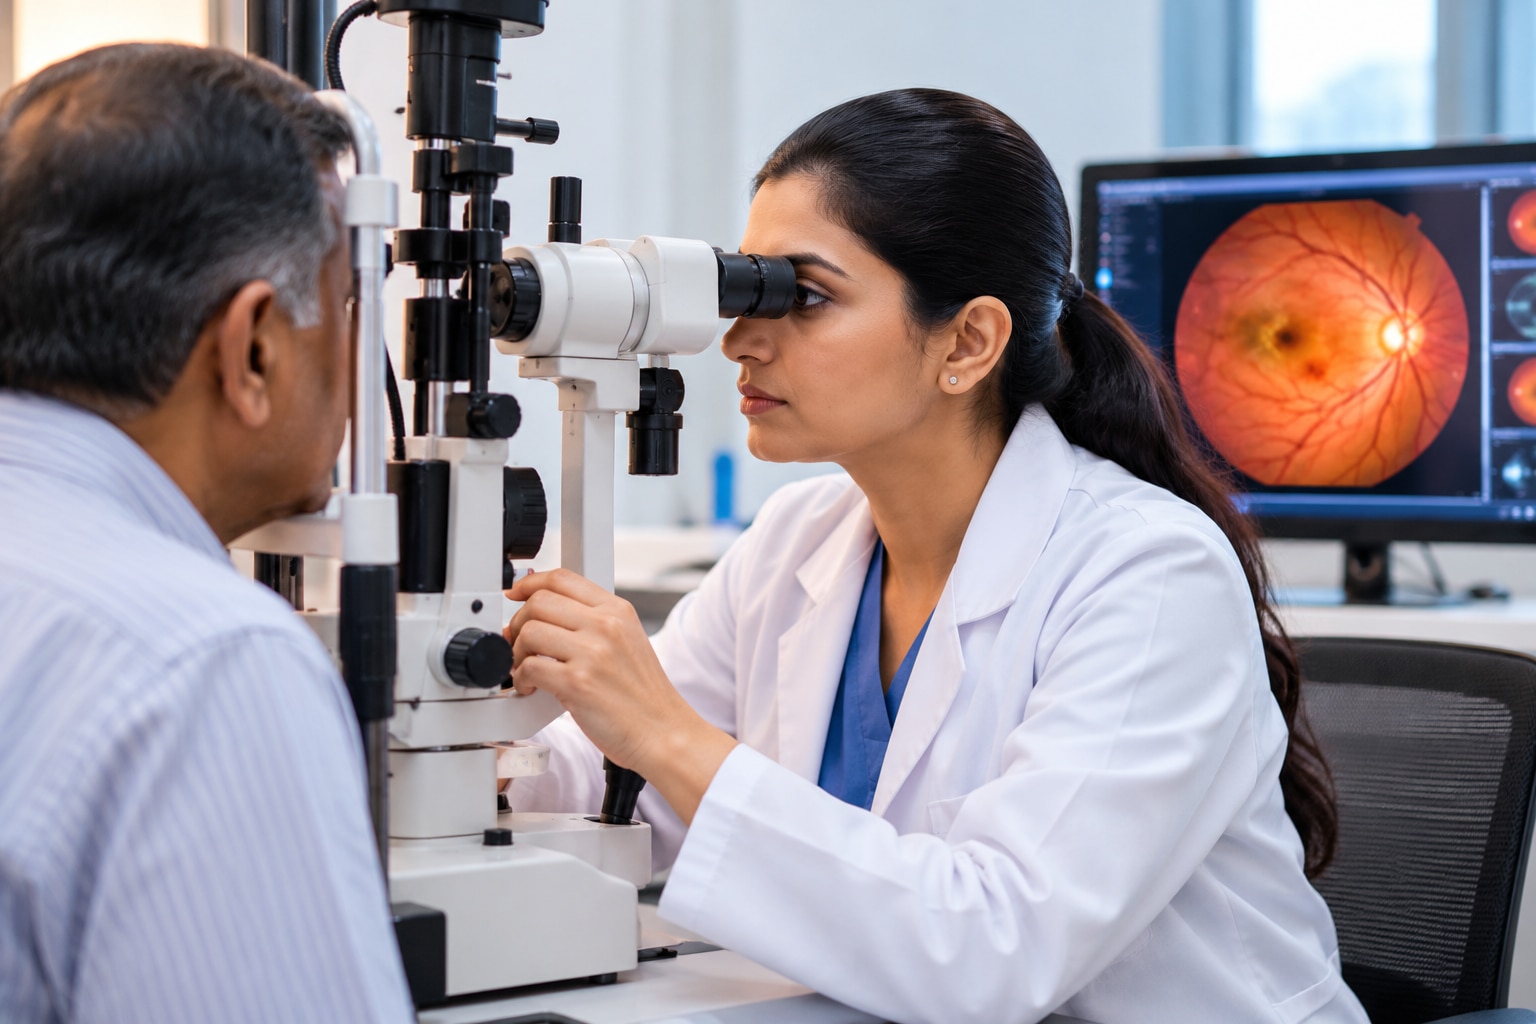
Retinal disorders range from fluid and bleeding that respond to injections to tears and detachments that need urgent repair. You will learn how to recognise time-critical symptoms, understand the tests behind a diagnosis, compare advanced treatments, and decide what ongoing monitoring each option requires.
Key takeaways
- Seek same-day assessment for flashes, new floaters, or a curtain over your vision.
- OCT, retinal photography, fluorescein angiography, and ultrasound confirm different retinal problems.
- Injections treat selected retinal swelling or abnormal blood vessels; laser and surgery address other causes.
- Observation is reasonable only when symptoms and imaging remain stable under planned review.
Which retinal symptoms need same-day assessment?
A stable retinal condition without new symptoms can follow its scheduled review. A sudden warning symptom needs same-day ophthalmic assessment; severe or abrupt vision loss requires immediate emergency care.
| Situation | Response | Why it matters |
|---|---|---|
| Stable known condition, unchanged vision | Keep the planned retinal review | Monitoring is appropriate when there is no new warning sign |
| Sudden flashes, an increase in floaters, or a curtain-like shadow | Seek same-day examination | These symptoms can indicate a retinal tear or early retinal detachment |
| Sudden central distortion or abrupt vision loss | Contact an ophthalmic emergency service immediately | Possible causes include retinal detachment, bleeding, or active macular disease |
A macula-on retinal detachment is especially time-sensitive. Repair before the detachment reaches the macula gives the central retina a better chance of preserving useful vision; do not wait for a scheduled appointment.
After an intravitreal injection, pain, increasing redness, light sensitivity, or a significant vision drop is not routine recovery. Seek urgent assessment for complications such as endophthalmitis, rather than waiting for the next injection visit.
Avoid driving when your vision is impaired. Arrange transport or call an ophthalmic emergency service, and report when the symptom began, which eye is affected, and whether it is worsening.
Which disorders are evaluated, and how are they confirmed?
Vitreo-retinal care evaluates disease in the vitreous gel and retina. Clinicians confirm a diagnosis by matching symptoms and visual acuity with examination findings and targeted imaging. The main disorders include:
- Diabetic retinopathy and diabetic macular oedema
- Age-related macular degeneration
- Retinal vein occlusion
- Posterior vitreous detachment
- Retinal tears
- Retinal detachment
- Macular hole
- Epiretinal membrane
| Examination | What it contributes | When it matters |
|---|---|---|
| Dilated fundus examination | Direct inspection of the retina, blood vessels, macula, and vitreous | Detecting tears, detachment, haemorrhage, new vessels, and membranes |
| Optical coherence tomography | Micrometre-scale cross-sections showing retinal layers, swelling, fluid, traction, or a hole | Assessing macular disease and monitoring structural change |
| Fundus photography | Records haemorrhages, exudates, vessels, and visible retinal changes | Comparing findings over time |
| Fluorescein angiography | Shows leakage, blocked vessels, and abnormal new vessels | Clarifying diabetic or vascular retinal disease |
| Ocular ultrasonography | Images the retina through blood, cataract, or another opacity | Investigating suspected retinal detachment when the fundus view is obscured |
An OCT image is not a stand-alone measure of useful vision. The clinician combines visual acuity, symptoms, examination findings, imaging, and disease context before recommending treatment; residual OCT abnormalities do not automatically mean another injection will improve sight.
How is advanced treatment matched to the retinal problem?
Advanced treatment means matching the procedure to the finding, not choosing the newest option. Intravitreal anti-VEGF injections treat diabetic macular oedema, neovascular age-related macular degeneration, and macular oedema from retinal vein occlusion. Treatment usually starts with repeated injections and is adjusted using vision, OCT fluid, bleeding, and recurrence.
1. For centre-involving diabetic macular oedema with visual impairment, baseline vision helps guide drug selection. In Protocol T, eyes starting at 20/50 or worse gained more average vision over two years with aflibercept than with bevacizumab or ranibizumab; differences were smaller when starting vision was better.
2. For selected macular oedema cases, corticosteroid treatment through an injection or implant is an alternative. It is not interchangeable with anti-VEGF treatment because cataract formation and raised eye pressure are important risks.
3. Retinal laser photocoagulation can seal a retinal tear before detachment. Panretinal photocoagulation treats high-risk proliferative diabetic retinopathy by treating peripheral retina, which can reduce peripheral or night vision; it is different from focal or grid laser for macular oedema.
4. Established retinal detachment needs pneumatic retinopexy, scleral buckling, pars plana vitrectomy, or a combination. Laser alone cannot reattach a detached retina.
An OCT image is not a measure of useful vision by itself. Clinicians combine visual acuity, symptoms, examination findings, OCT fluid, bleeding, and disease context; residual fluid does not automatically mean another injection will improve sight.
What do injections, laser, and retinal surgery involve?
An intravitreal injection usually takes minutes after numbing drops and antiseptic preparation. Expect brief pressure or scratching rather than sharp pain, followed by temporary irritation or floaters.
Treatment often starts with a loading series, then continues at intervals set by visual acuity, OCT fluid, bleeding, and recurrence; extending or stopping without monitoring can let disease activity return.
1. Laser photocoagulation seals a retinal tear before it progresses to detachment, or reduces abnormal peripheral vessels in proliferative diabetic retinopathy. It cannot restore photoreceptors damaged by ischaemia, prolonged detachment, or macular disease, and it cannot reattach an already detached retina.
You may need more than one session, with temporary blur and possible effects on peripheral or night vision.
2. Retinal surgery uses scleral buckling, pneumatic retinopexy, pars plana vitrectomy, or combinations according to the diagnosis. Vitrectomy removes vitreous gel to clear blood, relieve traction, remove an epiretinal membrane, close a macular hole, or repair a tear or detachment. Reattachment is an anatomical success, not a promise of normal central vision.
3. A gas bubble supports the retina while it heals; do not fly or travel to high altitude until it has gone, and tell every anaesthetist because nitrous oxide can expand it dangerously.
Silicone oil gives longer support but can cause cataract, raised eye pressure, corneal change, or recurrent retinal problems; removal is considered only when safe.
Recovery, discomfort, repeat procedures, and recurrence depend on the disorder, so follow-up visits remain essential.
When is observation reasonable, and how should you plan follow-up?
Observation is reasonable for a stable posterior vitreous detachment without a tear, a small finding without symptoms, or retinal disease without active fluid, bleeding, traction, or vision change.
It is not “do nothing”: follow the retinal specialist’s review interval and seek immediate reassessment for new flashes, a sudden increase in floaters, a curtain-like shadow, abrupt vision loss, or sudden central distortion.
| Option | What it means | When it applies |
|---|---|---|
| Observation | Scheduled examinations and imaging without immediate treatment | Stable findings, no symptoms, and no active retinal damage |
| Injection | Repeated medicine delivered into the eye | Recurrent fluid or bleeding from conditions such as macular oedema or neovascular disease |
| Laser | Seals a tear or reduces abnormal vessels | A retinal tear or selected vessel-related disease; it cannot reattach a detached retina |
| Surgery | Repairs structural retinal damage | Traction distorting the macula, obscuring bleeding, or retinal detachment |
Before accepting either plan, ask:
- Which diagnosis is present, and what does the scan show?
- What could happen if treatment is delayed?
- How many visits, scans, or injections are expected?
- Which symptoms signal recurrence or deterioration?
- Would another specialist opinion change the timing or treatment?
FOHS's K.B.H.Bachooali Charitable Eye&ENT Hospital in Parel can help coordinate this discussion when affordability, surgery planning, and ongoing monitoring matter. Inherited retinal disease requires genetic confirmation; voretigene neparvovec applies only to confirmed biallelic RPE65 mutation-associated retinal dystrophy, not retinal degeneration generally.
Related services
Vitreo Retinal Clinic K. B. Haji Bachooali Charitable Ophthalmic and ENT Hospital, located in Parel, Mumbai, offers comprehensive vitreo retinal services for the diagnosis... View service → |
Vitero Retina Clinic K. B. Haji Bachooali Charitable Ophthalmic and ENT Hospital, located in Parel, Mumbai, offers comprehensive retinal check-up services aimed at early... View service → |
Frequently asked questions
Which retinal symptoms need same-day assessment?
Flashes, a sudden increase in floaters, a curtain or shadow, distorted vision, or new vision loss needs same-day ophthalmic assessment. Severe or abrupt vision loss requires immediate emergency care.
Which retinal disorders are evaluated, and how are they confirmed?
Clinicians evaluate conditions such as retinal tears, retinal detachment, diabetic retinopathy, macular degeneration, macular oedema, and epiretinal membrane using examination, OCT, retinal photography, fluorescein angiography, or ultrasound when indicated.
How are injections, laser, and retinal surgery used?
Intravitreal injections target retinal swelling or abnormal blood vessels, laser seals selected retinal breaks or treats leaking vessels, and vitrectomy or other retinal surgery addresses problems that cannot be managed with medication or laser.
When is observation reasonable for a retinal condition?
Observation is reasonable when symptoms are stable, the retina is assessed as low risk, and imaging shows no change requiring treatment. Keep the scheduled follow-up and seek urgent review for new warning symptoms.